
Most people think of toe walking as something toddlers do and grow out of. So if you are an adult whose heels never quite touch the ground, or if someone has recently pointed out that you are walking differently, it is a strange thing to look up. Toe walking in adults falls into two very different groups, and telling them apart is the single most important thing you can do. One group is a long-standing mechanical problem that responds well to physiotherapy and stretching. The other is a signal that something in the nervous system has changed and needs a medical assessment first. This guide explains how to tell which one you are looking at, what it does to the rest of your body over time, and what treatment realistically achieves in an adult.
The Question That Matters Most: Is This New?
Before anything else, answer one question. Have you always walked this way, or did it start recently?
If you have toe walked since childhood and nothing has changed, you are most likely dealing with a long-standing mechanical pattern, often with a shortened calf and Achilles complex behind it. If you used to walk normally and this has developed over recent months or years, that is a different situation entirely. Neurological causes of toe walking are common, and identifying them changes the entire treatment plan, so ruling them out comes first [+].
The rest of this article is organised around that split, because almost every decision follows from it.
What Toe Walking Actually Is
The term describes a gait pattern rather than a disease, and defining it precisely helps you judge whether it applies to you.
A Missing Heel Strike
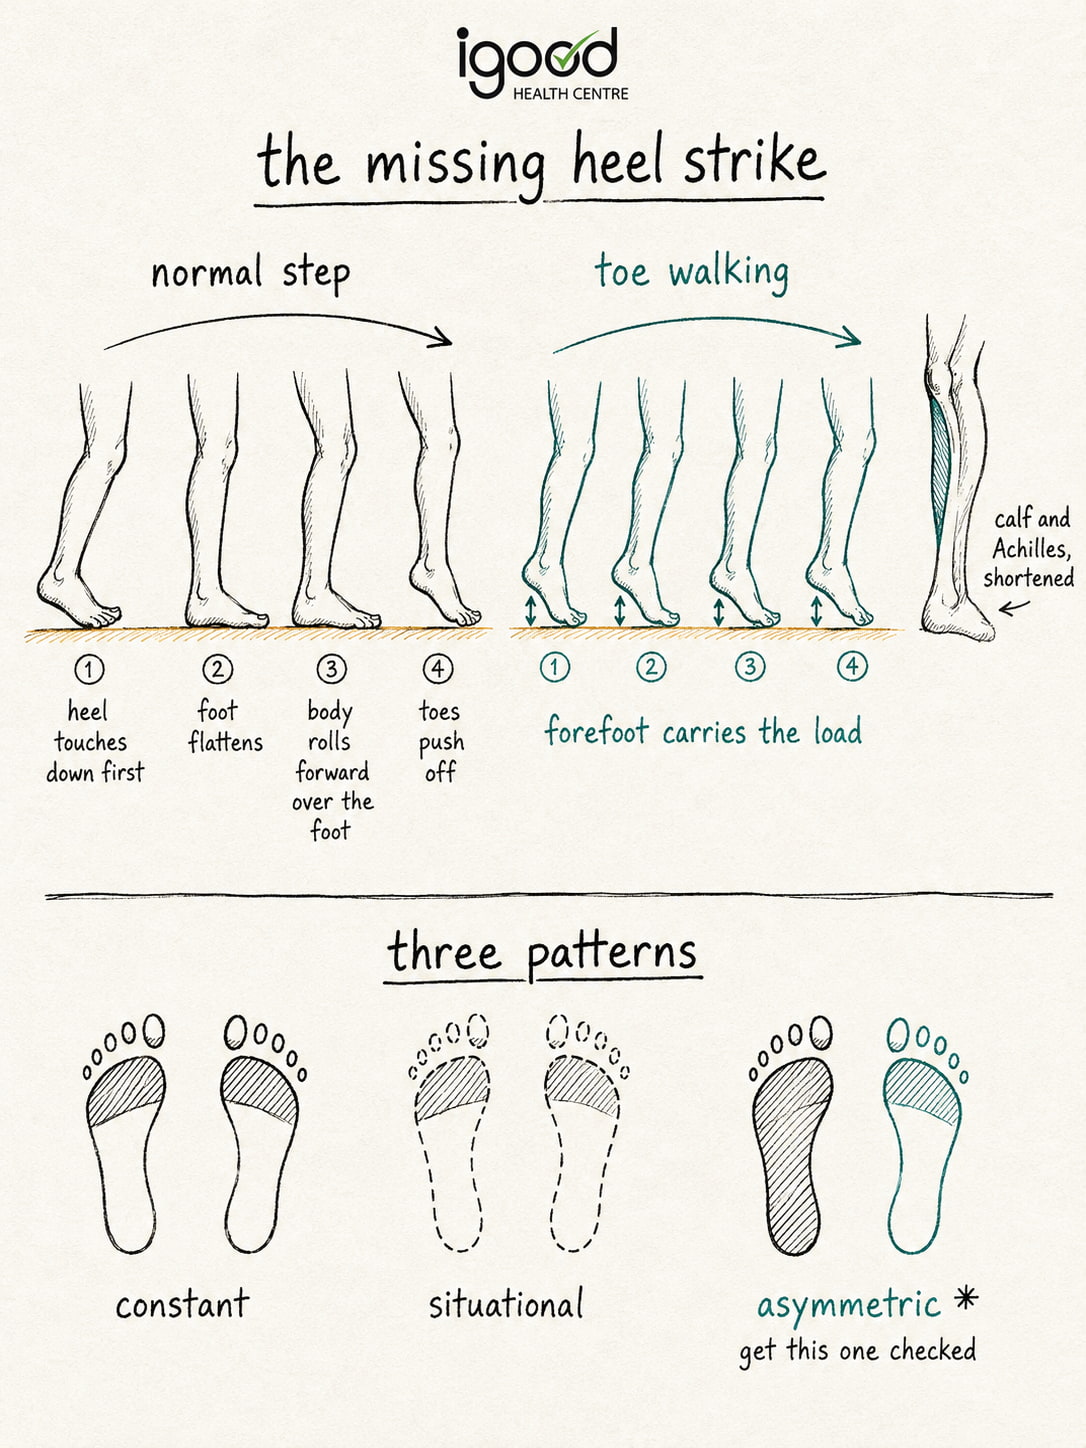
In a normal walking cycle, the heel contacts the ground first, the foot flattens, and the body rolls forward over the foot before the toes push off. Toe walking is the absence of that first heel contact. The forefoot lands first, the heel either never touches down or touches late, and the whole loading pattern of the leg shifts forward. Everything else about the condition follows from that one missing moment.
Full-Time and Part-Time Patterns
Very few adults toe walk one hundred percent of the time. It helps to notice your own pattern, because it points to different causes:
- Constant: heels rarely touch down, even standing still or walking slowly. More likely to involve a genuine physical restriction.
- Situational: appears when walking fast, barefoot, on hard floors, or when tired, but disappears when you concentrate. More likely habitual or sensory.
- Asymmetric: one side only. This is the pattern that most often points to a neurological or structural cause and deserves prompt assessment.
Can you stand flat-footed on command, with your knees straight, and hold it? If yes, the ankle still has range available and the pattern is at least partly a habit. If no, there is a physical restriction in the way.
Two Very Different Groups of Adult Toe Walkers
This is the central distinction of the whole topic. The two groups share a symptom and share almost nothing else.
| Lifelong toe walking | New in adulthood | |
|---|---|---|
| When it started | Childhood, often noticed before school age | Recently, over months or a few years |
| How it changes | Stable, or very slowly stiffer with age | Progressive, tends to get worse |
| Usual driver | Shortened calf and Achilles complex, habit | Change in nerve or spinal cord function |
| Sides affected | Usually both, fairly symmetric | Often one side first, or clearly uneven |
| First step | Gait and ankle assessment | Medical and neurological assessment |
If you are in the second column, read the red flag section before you book anything else. If you are in the first, the rest of this article is mostly about you.
Causes of Lifelong Toe Walking That Carries Into Adulthood
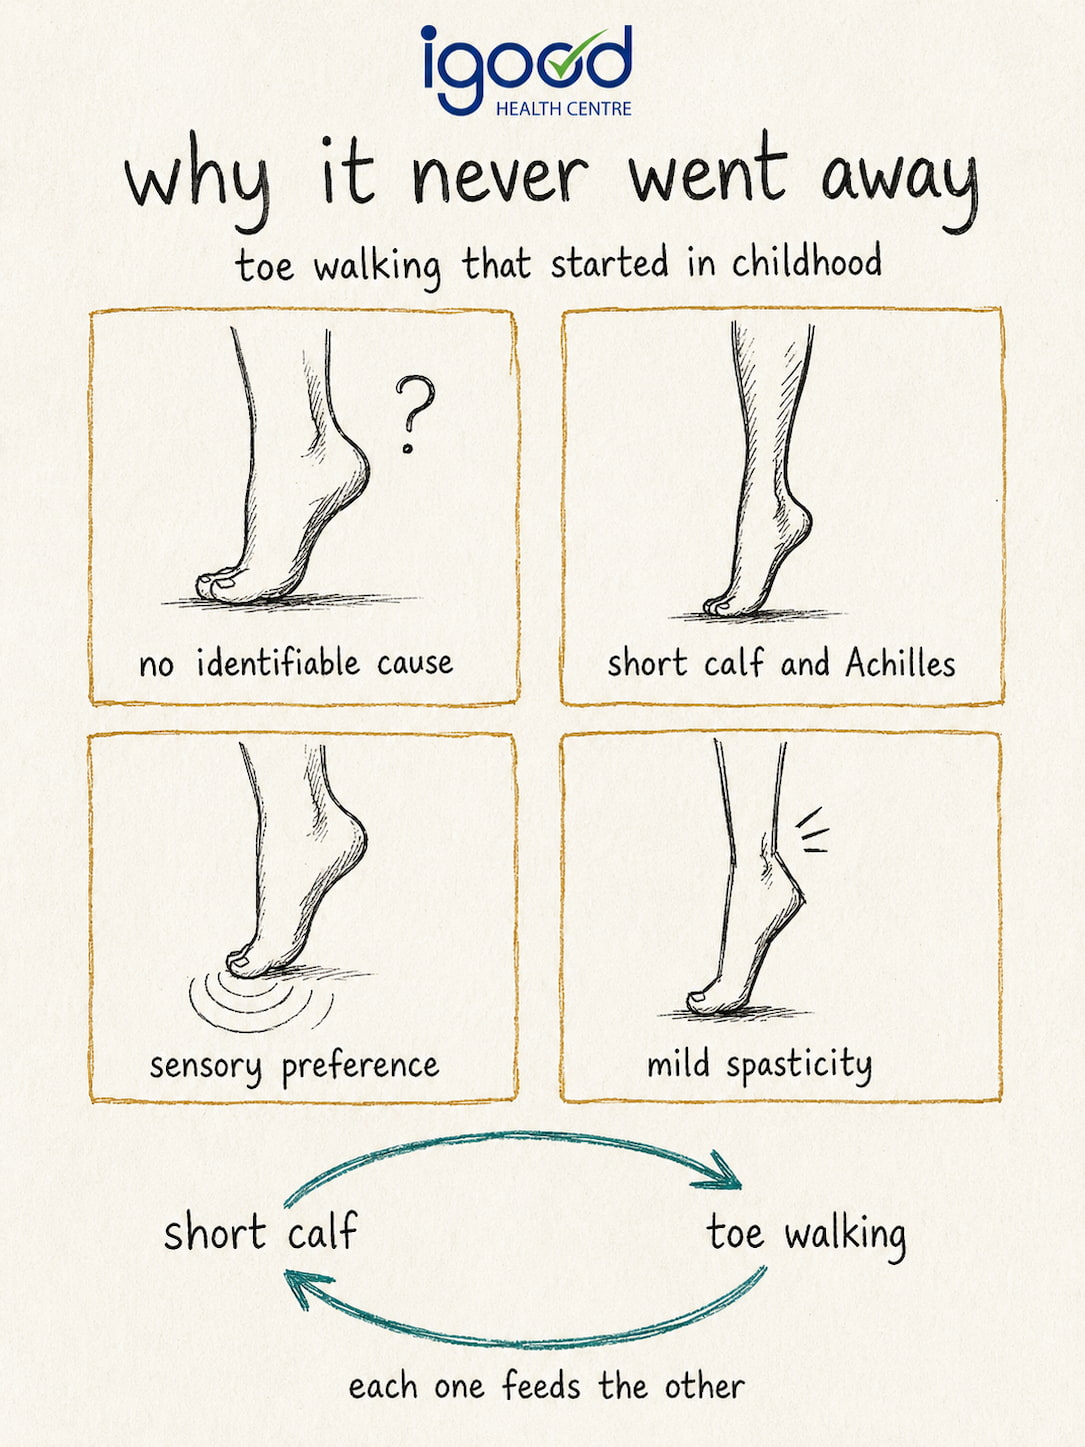
Adults in this group have usually been toe walking since before they can remember. The causes tend to overlap rather than stand alone.
Idiopathic Toe Walking That Never Resolved
Idiopathic toe walking means the pattern exists without any identifiable neurological, orthopaedic, or muscular disease behind it. It is a diagnosis of exclusion, made only after other causes have been ruled out [+]. Most cases resolve during childhood, but a proportion carry into adult life, sometimes without ever being formally assessed.
A Shortened Calf and Achilles Complex
The calf muscles merge into the Achilles tendon, which attaches to the heel bone. When that whole unit is short, the heel physically cannot reach the ground with the knee straight [+]. This can be the original cause of the toe walking or, just as often, a consequence of years of walking that way. One study of children, adolescents, and young adults found that those who toe walked had roughly three times the likelihood of severely restricted ankle range, and that the stiffness often extended to other joints as well [+].
This chicken-and-egg relationship matters clinically. By adulthood, the restriction is usually real regardless of how it started, and it has to be addressed on its own terms.
Sensory Processing and Neurodevelopmental Differences
Toe walking is more common in autistic people and in people with sensory processing differences, where the pattern is often linked to how the sole of the foot registers contact with the ground rather than to any tightness. Adults in this group frequently describe walking on the toes as simply feeling more comfortable or more grounded. Treatment aimed purely at stretching tends to miss the point here, and pressuring someone to change a self-regulating movement pattern is rarely the right goal.
Mild Cerebral Palsy Diagnosed Late or Never
Some adults with very mild spastic diplegia were never formally diagnosed, particularly if their function was good enough that nobody raised it. Toe walking with slightly stiff legs, a history of being described as clumsy, and a gait that has been the same since childhood can fit this picture. It is worth knowing, because it changes what treatment is realistic.
Causes of Toe Walking That Begins in Adulthood
This group deserves careful attention. Adult-onset toe walking is rarely a habit that appeared out of nowhere, and it is usually worth explaining rather than stretching.
Upper Motor Neuron Conditions
When the pathways carrying signals from the brain down the spinal cord are affected, the calf muscles become spastic and pull the foot into a pointed position. Hereditary spastic paraplegia is one example, and although some forms begin in childhood, later-onset forms can appear anywhere from young adulthood into the sixties, with a slow and progressive stiffening of the legs [+]. Toe walking is often one of the earliest signs, alongside exaggerated reflexes, leg cramps and spasms, and shoes that wear down unevenly over the big toe [+]. Multiple sclerosis and compression of the spinal cord in the neck can produce a similar picture.
Spinal Cord Tethering and Structural Cord Problems
A tethered spinal cord, where the cord is abnormally anchored to surrounding tissue, is a recognised cause of toe walking and can produce progressive weakness and tightness in the legs [+]. Signs on the lower back such as a dimple, a tuft of hair, or a patch of unusual pigmentation can point toward an underlying spinal cord or vertebral abnormality [+]. Some cases are only identified in adulthood after years of vague symptoms.
Peripheral Nerve Conditions
Charcot-Marie-Tooth disease and other inherited neuropathies change the balance of strength between the muscles that lift the foot and those that point it. The result can be a high-arched foot, a toe-first contact pattern, frequent tripping, and difficulty with balance in the dark. Reflexes here tend to be reduced rather than exaggerated, which is one of the ways a clinician tells the two categories apart.
Compensation After an Injury or Surgery
Not every case is neurological. After an ankle fracture, a significant sprain, an Achilles rupture, foot surgery, or a period in a walking boot, people often adopt a toe-first pattern to avoid loading a painful heel. The problem is that the pattern can outlive the injury by years, and the calf shortens quietly in the meantime. This is one of the more treatable groups, and it is also one of the most commonly missed.
Footwear and Habit
Years of daily high heels effectively hold the ankle in a shortened position for most of the waking day, and some people find that flat shoes become genuinely uncomfortable as a result. This alone does not usually produce true toe walking, but it does contribute to the calf tightness that makes a heel strike harder to achieve.
Red Flags: When Toe Walking Is Not a Biomechanics Problem
Any of the following alongside toe walking means a medical assessment should come before physiotherapy, massage, orthotics, or stretching programs. This is not a reason to panic, but it is a reason not to skip a step.
- Toe walking that is new in adulthood and has been getting worse
- One side clearly more affected than the other
- Leg stiffness, spasms, or cramps that come on at night
- Weakness, numbness, or tingling anywhere in the legs or feet
- Frequent tripping, or catching your toe on flat ground
- New bladder urgency, incontinence, or bowel changes
- Any change in coordination, speech, or hand function
- A family member with a similar progressive walking difficulty
The clinical reasoning behind these is straightforward. Brisk reflexes suggest a problem higher up in the nervous system, while reduced reflexes suggest a nerve or muscle problem, and either finding changes the entire plan [+]. A physician can check this in a few minutes.
What Years of Toe Walking Do to the Rest of the Body
Even where the cause is entirely benign, the mechanics have consequences, and they usually show up somewhere other than the ankle. This is why many adults arrive at a clinic for heel pain or knee pain without ever mentioning how they walk.
A Fixed Ankle Restriction
The most direct consequence is loss of ankle dorsiflexion, the ability to bring the toes up toward the shin. Over years this can move from a flexible tightness to a fixed contracture, and one school of thought holds that persistent toe walkers eventually develop a fixed ankle equinus in adulthood [+]. A flexible restriction responds well to stretching. A fixed one often does not.
Downstream Foot Problems
Restricted ankle motion has been linked in the foot and ankle literature to plantar fasciitis, Achilles tendinopathy, metatarsalgia, hallux valgus, and adult-acquired flatfoot [+]. The mechanism is simple. If the ankle cannot bend far enough, the heel lifts early in the step and the forefoot absorbs load it was not designed to carry.
This is worth knowing if you have been treated repeatedly for stubborn heel pain without lasting improvement. Our page on ankle and foot pain treatment covers those conditions in more detail.
Knee, Hip, and Lower Back Load
The forward shift in loading does not stop at the foot. The knee tends to work harder to control each step, the pelvis and lower back adjust to keep the trunk upright, and the calf muscles stay under near-constant demand. Adults who have toe walked for decades often report calf fatigue and cramping as much as foot pain.
Balance and Falls
Walking without proper heel contact reduces the size of the base you are balancing over. Constant toe walking can produce lasting changes to the structure of the foot and increases the risk of falling [+]. This becomes more relevant with age, and it is one of the stronger practical arguments for addressing the pattern even when it is not painful.
The Social and Self-Consciousness Side
This is rarely discussed in clinical settings but frequently raised by patients. An unusual gait draws attention, and social stigma is a recognised consequence of persistent toe walking [+]. It is a legitimate reason to seek help, and it does not need to be justified with a pain score.
How Adult Toe Walking Is Assessed
A useful assessment answers three questions in order: is this neurological, is the restriction flexible or fixed, and where exactly is the tightness coming from.
The Neurological Screen Comes First
Reflexes, muscle tone, strength, sensation, and coordination are checked before anything else. Asymmetry, brisk reflexes, or weakness redirect the whole process toward medical investigation, which may include imaging of the brain or spine. Getting this order right is what separates a thorough assessment from a superficial one.
Separating Gastrocnemius From Soleus
The calf has two main muscles. Gastrocnemius crosses both the knee and the ankle, while soleus crosses only the ankle. The Silfverskiold test measures ankle dorsiflexion first with the knee straight and then with the knee bent. If the range improves noticeably when the knee bends, the restriction sits in the gastrocnemius. If it does not improve, the deeper soleus and the Achilles are involved too [+]. That distinction directly determines which stretches will work and which will not, so it is worth asking your clinician which pattern you have.
Watching You Actually Walk
Gait observation catches things a static examination misses. Research using detailed motion analysis has found that toe walkers show measurable changes in walking speed and in how long they spend on each leg, even when they look reasonably normal at a glance [+]. In a clinic setting this means being watched walking barefoot, walking fast, and turning, not just standing still.
Checking Your Shoes
An underrated diagnostic step. Uneven wear concentrated at the front of the sole confirms the pattern and shows how long it has been going on. Wear over the big toe area in particular has been described as a characteristic sign in spastic gait patterns.
Treatment Options and What Each One Realistically Does
Treatment depends almost entirely on the cause and on whether the ankle restriction is still flexible. Below is the usual ladder, from least to most invasive.
Conservative Care
This is where most adults with a flexible restriction and no neurological findings will start, and where the best value sits.
- Calf stretching, targeted correctly: with the knee straight for gastrocnemius and with the knee bent for soleus. Sustained holds, done daily over months rather than weeks.
- Eccentric calf loading: slow heel lowering off a step, which builds tolerance in the muscle and tendon rather than just lengthening it.
- Gait retraining: deliberate practice of heel-first walking, usually starting slowly and on flat ground with cueing, then generalising to normal speed.
- Manual therapy: soft tissue work on the calf and plantar fascia to reduce tone and make stretching more productive. Useful as a companion to the active work rather than a treatment on its own.
- Strengthening the front of the shin: the muscles that lift the foot are usually underused, and strengthening them supports the new pattern.
- Night splints: hold the ankle in a lengthened position during sleep, adding hours of gentle stretch without extra effort.
Footwear and orthotic support also play a role, particularly where the forefoot has been overloaded for years. A gait assessment combined with custom orthotics can redistribute pressure while the underlying pattern is being worked on.
Medical Options When Conservative Care Stalls
Serial casting, where the ankle is progressively brought into a more neutral position over several cast changes, is used more often in children but is sometimes applied in adults with a partly flexible restriction. Botulinum toxin injections into the calf can reduce spasticity in neurological cases and create a window in which stretching becomes more effective. Neither is a first-line option, and both require a physician.
Surgical Lengthening
Where the contracture is fixed and function is genuinely limited, surgical lengthening of the gastrocnemius or the Achilles is considered. It is effective at restoring range, but recovery involves months of rehabilitation, and it does not by itself retrain the walking pattern. This is reserved for cases that have not responded to a proper conservative trial.
When the Cause Is Neurological
Where an underlying neurological condition is driving the pattern, treatment focuses on managing the condition itself, and physiotherapy plays a supportive role in maintaining mobility, strength, range of motion, and endurance while reducing cramps and spasms [+]. Muscle relaxants prescribed by a physician are often part of the picture. The goal shifts from correcting the gait to protecting function.
Realistic Expectations for an Adult
Honest framing here prevents a lot of wasted effort, and it is the part most articles skip.
- Adults change more slowly than children. Growing tissue responds to lengthening in a way that mature tissue does not. Expect to think in terms of months, not weeks.
- Flexible restrictions respond well. If you can get your heel down with the knee bent, there is real range to recover through consistent work.
- Fixed contractures usually do not resolve with stretching alone. You can improve comfort and reduce downstream pain, but restoring full range typically needs a medical or surgical route.
- The habit outlasts the tightness. Many adults regain the range and still walk on their toes out of decades of motor memory. Gait retraining is a separate piece of work from stretching, and it is the piece people skip.
- Reducing pain is often the more useful goal. For plenty of adults, resolving the heel pain, calf cramping, and forefoot overload matters more than achieving a textbook heel strike.
Getting Assessed in Richmond Hill
If you are local and want to take this further, here is what the process usually looks like and what is worth knowing before you book.
Where to Start
If anything on the red flag list applies, start with your family physician so a neurological cause can be ruled in or out. If your toe walking is lifelong, stable, symmetric, and you have no neurological symptoms, a gait and biomechanical assessment is a reasonable first step.
- In Ontario you do not need a physician referral to see a physiotherapist, chiropractor, or Registered Massage Therapist directly
- Assessment and treatment are covered by most extended health plans, and many clinics including ours offer direct billing
- Custom orthotics generally require a prescription for insurance coverage even though OHIP does not cover them, so check your plan before committing
- If your gait changed after a workplace injury or a car accident, treatment may be funded through WSIB or your auto insurer, which our injury and rehabilitation programs are set up to handle
A Practical Note for Ontario Winters
Toe walking reduces the contact area between you and the ground, and that becomes a genuine safety issue on ice. Patients from across Richmond Hill neighbourhoods including Oak Ridges, Bayview Hill, Mill Pond, Jefferson, Crosby, and Langstaff, as well as nearby Thornhill, Markham, Vaughan, and Aurora, often notice their balance is worst between December and March. Winter boots with a wide, flat, well-gripped sole and a modest heel drop make more difference than most people expect, and this is one of the few interventions that helps immediately.
What a First Appointment Involves
Expect a history covering when the pattern started and whether it has changed, a neurological screen, ankle range measured both with the knee straight and bent, a look at your footwear, and observation of your walking. You should leave with a clear answer about whether your restriction is flexible or fixed, and a home program rather than a generic handout. You can review the clinical team at our Richmond Hill clinic before booking.
Frequently Asked Questions
These are the questions adults ask most often once they start looking into this.
Can adults stop toe walking?
Many can, particularly where the ankle restriction is still flexible and there is no neurological cause. It takes consistent stretching over months combined with deliberate gait retraining, because regaining range does not automatically change a decades-old walking habit. Fixed contractures are less likely to resolve without medical or surgical input.
Is toe walking in adults dangerous?
The pattern itself is not dangerous, but two things about it matter. It increases fall risk by reducing stability, and it drives downstream foot, knee, and back problems over time. More importantly, if it is new, it can be the first visible sign of a neurological condition that benefits from early diagnosis.
Why do my calves cramp so much?
Because they are working almost continuously. In a normal step, the calf gets a brief moment of lengthening and relative rest at heel contact. Toe walking removes that moment, so the muscle spends far more of the day under load. Night cramps are a common consequence, though persistent night cramps and spasms should also be mentioned to a physician.
I only toe walk when I am barefoot. Is that a problem?
It is usually a milder version of the same picture and often has a sensory component. It is worth having the ankle range measured, because a restriction can be present even when the pattern is only situational, but a barefoot-only pattern is generally less concerning than a constant one.
Will stretching alone fix it?
Stretching addresses the length of the muscle, not the motor pattern. It is necessary but rarely sufficient in an adult. Combining stretching with strengthening of the muscles that lift the foot, plus deliberate practice of heel-first walking, produces far better results than stretching on its own.
Should I try to force my child or teenager to stop toe walking?
This article is about adults, and persistent toe walking in a child should be assessed by a healthcare provider rather than managed through correction at home. Forcing the pattern to change without knowing the cause can be counterproductive, particularly where there is a sensory or neurological component.
