
If you cannot reach your seatbelt, fasten a bra strap, or lie on one side without waking up, you already know that frozen shoulder is not ordinary stiffness. It is also the kind of problem where everyone offers a different opinion, so it is fair to ask whether massage therapy works for frozen shoulder or whether it is simply a pleasant hour that changes nothing. The honest answer sits somewhere in the middle, and it depends almost entirely on which stage your shoulder is in. This guide walks through what massage can genuinely reach inside a frozen shoulder, what it cannot touch, how to tell whether your shoulder is even frozen in the first place, and what a realistic treatment plan looks like.
The Short Answer: Massage Reaches the Muscles, Not the Capsule
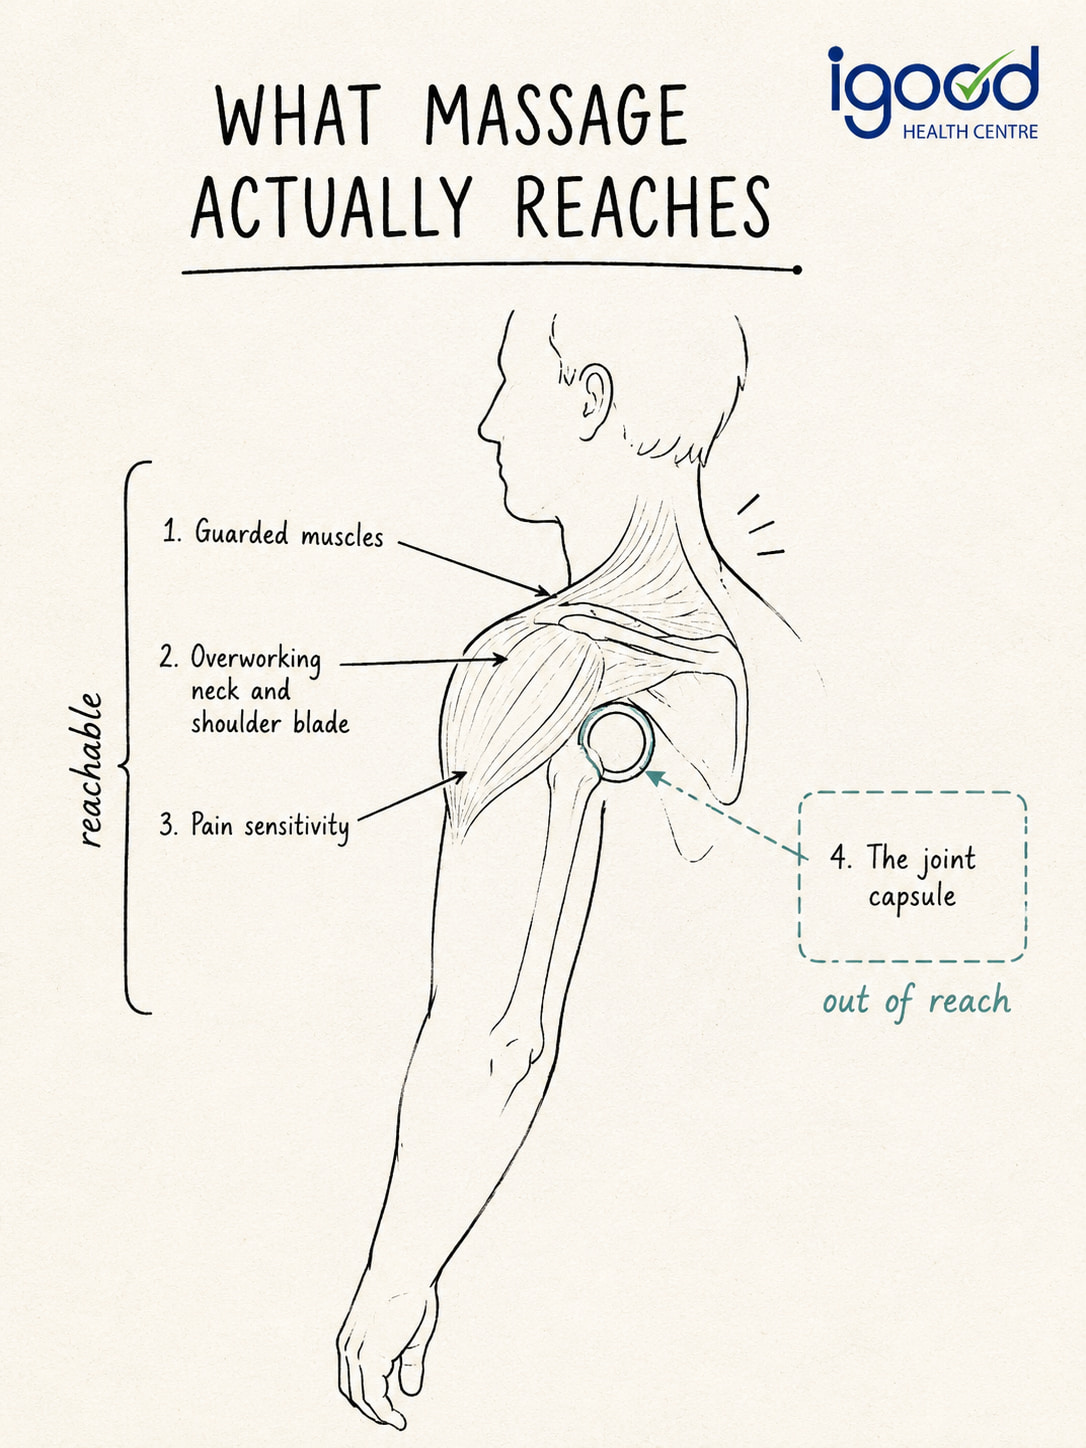
Frozen shoulder is a problem inside the joint capsule, which is the sleeve of connective tissue wrapped around the ball-and-socket joint. That sleeve becomes inflamed, thickened, and progressively tighter, and no amount of pressure applied through the skin and muscle will stretch it open [+]. What massage therapy does very reliably is work on everything layered over that capsule: the guarded muscles, the overworked neck and shoulder blade, and the pain sensitivity that builds up over months of poor sleep.
So the useful way to frame the question is not “does massage cure frozen shoulder” but “which parts of my problem can massage actually change.” Here is the split:
| What massage therapy can change | What it cannot change |
|---|---|
| Pain levels and muscle soreness around the joint | The thickened, contracted joint capsule itself |
| Protective muscle guarding and spasm | The overall length of the condition |
| Stiffness in the neck, upper back, and chest wall | Underlying diabetes or thyroid disease driving it |
| Sleep quality and tolerance for stretching | Structural damage such as a rotator cuff tear |
| Movement of the shoulder blade on the rib cage | The need for injection or surgery in stubborn cases |
That is a meaningful list, and it explains why so many patients report feeling better after a session even though their shoulder still will not lift. The relief is real. It is just aimed at the secondary problems rather than the primary one.
What Frozen Shoulder Actually Is?
Frozen shoulder has a formal name, adhesive capsulitis, and understanding the mechanism makes every treatment decision easier to judge. It is not a muscle knot that got out of hand, and it is not something you caused by sleeping awkwardly.
The Restriction Lives in the Joint Capsule, Not the Muscles
In a healthy shoulder, the capsule is loose enough to let the arm move in almost every direction. In frozen shoulder, an inflammatory process causes the capsule to thicken and fibrose, bands of tissue called adhesions form, and the amount of lubricating synovial fluid inside the joint drops. The result is a joint that has been physically shrink-wrapped [+]. This is why the loss of movement is so complete. It is a mechanical block, not weakness or unwillingness.
Primary and Secondary Frozen Shoulder Are Not the Same Problem
Clinicians separate frozen shoulder into two groups because they behave differently and respond differently to treatment [+]. Knowing which one you have changes how aggressive treatment should be.
- Primary (idiopathic): appears with no clear trigger. It is linked to systemic conditions and tends to follow the classic three-stage pattern.
- Secondary: follows a specific event such as a fracture, rotator cuff surgery, a period of immobilisation in a sling, or breast cancer surgery involving the armpit.
Secondary cases often need a slightly different approach, because there is usually a second problem sitting underneath the stiffness that also needs attention.
Who Tends to Develop It
Frozen shoulder affects roughly two to five percent of the general population, and the risk is meaningfully higher in people with diabetes, who also tend to have more severe symptoms and a longer recovery period [+]. It shows up most often between the ages of 40 and 60, and more frequently in women than men. Thyroid conditions are the other common association [+].
If you fall into one of these groups and one shoulder has been gradually losing motion over several weeks, it is worth getting assessed early rather than waiting to see whether it settles on its own.
Is It Really Frozen Shoulder? Conditions That Look Almost Identical
This section matters more than most people expect. Massage therapy is a reasonable choice for a genuinely frozen shoulder, but it can be the wrong first step for several of the conditions that imitate it. A stiff, painful shoulder is a symptom, not a diagnosis.
| Condition | How it differs from frozen shoulder | Typical clue |
|---|---|---|
| Rotator cuff tear or tendinopathy | Weakness dominates rather than stiffness, and someone else can often move your arm further than you can. | Passive movement is much better than active movement |
| Subacromial impingement | Pain appears in a specific arc of movement rather than throughout the whole range. | Hurts overhead, comfortable at rest |
| Shoulder osteoarthritis | Stiffness is real, but it usually comes with grinding and shows up on X-ray. | Crepitus and visible joint changes on imaging |
| Neck-related (cervical) referred pain | The shoulder joint itself moves normally when tested carefully. | Pain travels down the arm and may include tingling |
The One Finding That Separates Frozen Shoulder From the Rest
The defining feature of adhesive capsulitis is loss of both active and passive movement, meaning your arm is just as stuck when a clinician moves it for you as when you move it yourself [+]. External rotation, the movement of turning your forearm outward with your elbow tucked at your side, is usually the most restricted direction of all [+]. In a rotator cuff problem, by contrast, a clinician can normally move your arm through a much larger range than you can move it yourself. That single distinction shapes most of the treatment plan.
How Massage Therapy Acts on a Frozen Shoulder
Once you accept that the capsule is out of reach, the value of massage becomes much clearer. It works on four levels, and each one addresses a real part of the problem.
It Reduces Protective Muscle Guarding
When a joint hurts every time it moves, the surrounding muscles contract to stop that movement from happening. This guarding is automatic and protective, but after a few months it becomes its own source of pain and adds stiffness on top of the capsular restriction. Soft tissue work that calms the deltoid, rotator cuff, and surrounding musculature reduces this extra layer of tension so the shoulder is not fighting itself.
It Unloads the Muscles Doing the Extra Work
When the shoulder joint stops contributing, the body borrows movement from everywhere else. That borrowed movement is why so many frozen shoulder patients also develop neck pain and headaches. The usual suspects are:
- Upper trapezius and levator scapulae, which hike the shoulder blade upward to fake overhead reach
- Pectoralis minor, which tips the shoulder blade forward and pulls the shoulder into a rounded position
- Latissimus dorsi and teres major, which tighten and further block external rotation
- The muscles on the opposite side, which take over daily tasks and become overloaded in turn
These structures are all fully accessible to hands-on treatment, and releasing them can restore a surprising amount of usable arm movement even while the capsule itself is unchanged. Approaches such as myofascial release therapy are commonly used for exactly this purpose.
It Changes Pain Processing, Not Just Tissue
Months of disrupted sleep and constant pain make the nervous system more sensitive, so the same stimulus starts to hurt more than it did at the beginning. Massage has a well-documented calming effect on this system. It lowers perceived pain intensity, reduces the stress response, and often improves sleep. Better sleep on its own tends to lower pain scores the following day, which makes stretching and rehabilitation far more tolerable.
What Massage Cannot Reach: The Contracted Capsule
Adhesive capsulitis involves progressive contraction of the glenohumeral joint capsule, and the thickened coracohumeral ligament at the front of the joint is a particular barrier to external rotation [+]. These structures sit deep inside the joint, underneath the rotator cuff. No massage technique, however firm, applies a meaningful stretch to them. Anyone promising to “break up the adhesions” with pressure is describing something that does not happen mechanically.
Does It Work? Looking at Each Outcome Separately
“Does it work” only becomes answerable once you specify what you want it to do. Massage performs very differently across the four outcomes patients actually care about.
| Outcome | What to realistically expect | How strong is the case |
|---|---|---|
| Pain | Noticeable reduction, often felt the same day, though it may fade between sessions early on | Strongest area of benefit |
| Range of motion | Small gains, mostly from a freed-up neck, shoulder blade, and chest wall rather than the joint itself | Modest, and only as an add-on to exercise |
| Daily function and sleep | Meaningful improvement in dressing, reaching behind the back, and sleeping on the affected side | Consistently reported by patients |
| Length of the condition | No evidence that it shortens the overall course | Not supported |
Pain Relief Is Where the Effect Is Strongest
This is the outcome massage handles best, and it is not a trivial one. Pain is what wakes you at three in the morning, what stops you from doing your home exercises properly, and what makes the whole condition feel unmanageable. Reducing it changes how well every other part of your treatment works.
Range of Motion Improves Modestly, and Only as an Add-On
Research on adding soft tissue techniques to standard rehabilitation shows mixed results. Some trials of instrument-assisted soft tissue mobilization report improvements in mobility and function when it is added to conventional physiotherapy [+], while broader reviews of exercise-based care have found no clear additional benefit from layering instrument-assisted soft tissue massage on top of exercise. The reasonable interpretation is that massage supports the exercise program rather than replacing any part of it.
Function and Sleep Often Improve Before Motion Does
Patients frequently report that they can dress themselves more easily and sleep through the night well before their measured range of motion changes. That gap makes sense. Much of what limits daily tasks is pain and guarding, not the raw number of degrees available at the joint.
It Will Not Shorten the Condition
This is the part patients least want to hear, and the part that separates honest advice from marketing. Frozen shoulder is largely self-limiting, but recovery commonly takes more than two years, and it is slower still in people with diabetes or thyroid problems [+]. Some people are left with a small amount of permanent stiffness. Treatment makes the journey considerably more comfortable and protects your function along the way. It does not fast-forward the timeline.
Massage Therapy by Stage: The Most Important Variable
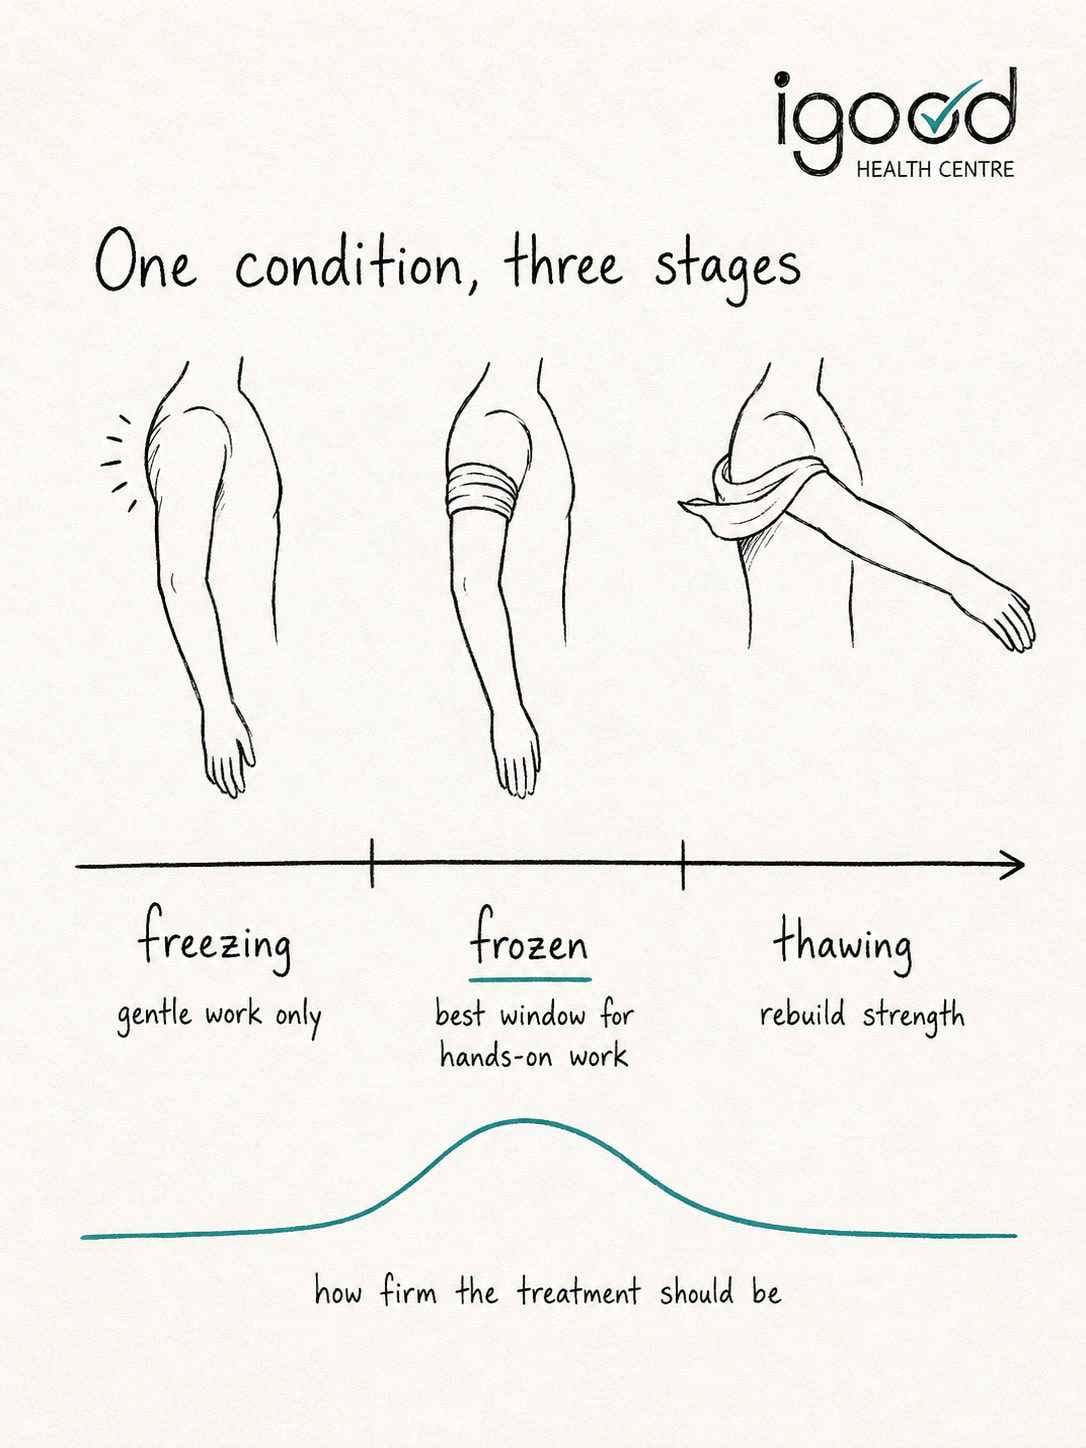
Frozen shoulder progresses through three fairly predictable stages, and treatment should be matched to the stage rather than applied the same way throughout [+]. Getting this wrong is the main reason some people say massage made their shoulder worse.
| Stage | Typical duration |
Role of massage therapy |
|---|---|---|
| Freezing (painful) | 6 weeks to 9 months | Gentle, pain-focused work only. Firm pressure and end-range stretching tend to flare the joint and set progress back. |
| Frozen (stiff) | 4 to 6 months | The highest-value window. Pain has usually settled, so soft tissue work pairs well with stretching and joint mobilisation. |
| Thawing (recovery) | 6 months to 2 years | A supportive role. Focus shifts to restoring shoulder blade mechanics and rebuilding strength. |
Those stage durations come from orthopaedic guidance and give a realistic sense of the timeline you are working with [+].
Freezing Stage: Less Is More
During the painful stage the joint is inflamed and irritable. The instinct is to push through and stretch harder, and that instinct is wrong here. Massage should stay light, focus on the neck, shoulder blade, and upper back rather than digging into the joint line, and aim purely at pain relief and sleep. Any technique that leaves the shoulder aching for the rest of the day was too much.
Frozen Stage: The Best Window for Hands-On Work
By this stage the pain has usually calmed down but the stiffness is at its worst. Deeper soft tissue work becomes both tolerable and useful, particularly when it is delivered immediately before stretching or joint mobilisation while the tissue is warm and less reactive. This is where combining massage with an active rehabilitation program pays off most.
Thawing Stage: Rebuilding Rather Than Releasing
Movement returns gradually during this phase, and the priority shifts. Months of compensation have left the shoulder blade moving poorly and the rotator cuff weak. Massage still helps with residual tightness, but strengthening and movement retraining should take the lead. Stopping treatment as soon as the pain disappears is a common way to end up with lingering stiffness.
Which Massage Techniques Are Used for Frozen Shoulder
Registered Massage Therapists draw on several approaches, and the choice depends far more on your stage and irritability than on any one technique being inherently superior.
- Swedish and relaxation-based massage: broad, rhythmic strokes aimed at pain relief and calming the nervous system. Best suited to the painful freezing stage.
- Deep tissue and trigger point therapy: targeted pressure on tight bands in the trapezius, levator scapulae, infraspinatus, and pectoral muscles. Better tolerated during the frozen stage.
- Myofascial release: sustained gentle pressure into fascial restrictions, often around the chest wall and shoulder blade, where tightness limits usable movement.
- Active release techniques: pressure applied while the arm is guided through movement, which addresses tissue that has stiffened through disuse.
- Instrument-assisted soft tissue mobilization: handheld tools used to apply controlled shear force to superficial tissue. Evidence is mixed, and it is not appropriate during an irritable phase.
Most sessions blend several of these rather than sticking to a single label. If you want a closer look at what one specific approach involves, active release therapy is a good example of how movement and pressure are combined.
Massage Therapy and Joint Mobilization Are Different Things
This distinction causes a lot of confusion. Massage therapy works on soft tissue: muscle, fascia, and tendon. Joint mobilization is a graded gliding force applied directly to the joint surfaces to address capsular restriction, and it is delivered by physiotherapists and chiropractors within their scope of practice. For frozen shoulder specifically, joint mobilization targets the actual problem while massage targets everything around it. That is exactly why the two are usually combined rather than treated as alternatives.
Massage Alone, or Massage Combined With Other Care?
Very few frozen shoulders are best managed with massage on its own. Thinking of care as a ladder makes it easier to work out where you currently sit and when it is time to escalate.
- Massage therapy alone. Reasonable if your main complaint is pain and muscular tension and your stiffness is mild or still early in the freezing stage. Not sufficient as a long-term plan.
- Massage plus an exercise-based program. This is the combination with the strongest support. Physiotherapy focused on flexibility and range of motion is the primary non-surgical recommendation for frozen shoulder, and soft tissue work makes those sessions more productive and more comfortable [+].
- Adding medical management. When pain is severe or progress stalls, a corticosteroid injection can reduce pain and improve range of motion [+], and hydrodilatation uses fluid to stretch the capsule from the inside. Manual therapy usually works better in the weeks following these procedures.
- Surgical options. Manipulation under anaesthetic or arthroscopic capsular release is considered when conservative care over several months has not helped [+]. Rehabilitation afterwards is essential, and massage often plays a role in it.
If your case is connected to a workplace injury or a motor vehicle accident, coordinated care across disciplines matters even more, both clinically and administratively. Our injury and pain management programs are built around that kind of multidisciplinary approach.
When Massage Therapy Is Not the Right Choice
Massage is a low-risk treatment, but low risk is not the same as no risk, and there are situations where it should be delayed or skipped entirely. A Registered Massage Therapist will screen for these, and you should mention anything relevant before the session begins.
Situations That Rule Out Treatment for Now
These are absolute reasons to postpone hands-on work over the shoulder until they are resolved or cleared by a physician.
- Suspected fracture or dislocation, or an unexplained deformity in the shoulder
- Active infection, fever, or a hot and visibly swollen joint
- Deep vein thrombosis or an active blood clot anywhere in the body
- Open wounds, active skin infection, or a rash over the treatment area
- An unexplained lump or swelling that has not been medically assessed
Cautions Worth Raising Before the Session Starts
These do not prevent treatment, but they should change how the session is delivered.
- Uncontrolled diabetes, which is associated with more severe symptoms and slower recovery and usually calls for a gentler approach
- A corticosteroid injection within the past week or two, since the area is often best left settled for a short period
- Blood-thinning medication, which makes bruising more likely with firm pressure
- An acute inflammatory flare with severe night pain, which usually means the shoulder is too irritable for deep work
- Osteoporosis or recent shoulder surgery, both of which limit how much force is appropriate
Signs That Need Medical Assessment First
If any of the following apply to you, arrange a medical assessment before booking soft tissue treatment.
- Shoulder pain that started after a significant fall or impact
- Numbness, tingling, or weakness travelling down the arm into the hand
- Unexplained weight loss, night sweats, or a history of cancer alongside new shoulder pain
- Chest pain, jaw pain, or shortness of breath accompanying left shoulder pain, which requires emergency care
What a Realistic Course of Treatment Looks Like in Richmond Hill
Knowing the theory is useful. Knowing what actually happens week to week is more useful. Here is what patients across Richmond Hill neighbourhoods including Bayview Hill, Oak Ridges, Mill Pond, Jefferson, Crosby, Doncrest, and Langstaff, as well as nearby Thornhill, Markham, Vaughan, and Aurora, typically experience.
Session Length, Frequency, and Coverage
Sessions usually run 30 to 60 minutes. In the painful early phase, weekly visits are common because the effect of each session tends to wear off quickly. As the shoulder settles into the frozen stage, spacing sessions to every one or two weeks while doing daily home exercises is usually more effective than frequent passive treatment.
- In Ontario you do not need a physician referral to see a Registered Massage Therapist or a physiotherapist, so you can book an assessment directly
- Massage therapy provided by an RMT is covered by most extended health plans, and many clinics including ours offer direct billing
- If your shoulder problem stems from a workplace injury or a car accident, treatment may be funded through WSIB or your auto insurer rather than your extended health plan
What Changes, and Roughly When
Setting expectations properly prevents the frustration that makes people quit halfway through. A typical pattern looks like this:
- Sessions 1 to 3: noticeable pain relief lasting a day or two, better sleep, and no meaningful change in range of motion yet.
- Weeks 3 to 6: relief lasts longer between sessions, neck and upper back tension eases, and small functional wins appear such as reaching a back pocket.
- Months 2 to 4: range of motion begins improving if you are in or entering the frozen stage and doing your home program consistently.
- Beyond that: progress tracks the natural course of the condition, with treatment protecting your function and comfort along the way.
What You Do Between Sessions Matters More Than the Sessions
This is the single biggest predictor of how well a frozen shoulder recovers. One hour of treatment per week cannot outweigh 167 hours of a shoulder held still. Ontario winters make this harder than it sounds. Cold weather, heavy coats, and months of reduced outdoor activity all encourage guarding and stiffness, and shovelling season adds a genuine risk of flare-ups if you are not careful with technique. A short daily routine of gentle range-of-motion work, kept well within a pain-tolerable range, does more than any single treatment session.
Your provider should give you a specific home program rather than a generic handout. If you want to know who you would be working with, you can review the clinical team at our Richmond Hill clinic before booking.
Frequently Asked Questions
These are the questions patients ask most often once they understand what frozen shoulder actually is.
Can massage make frozen shoulder worse?
It can, if the pressure or stretching is too aggressive during the inflamed freezing stage. Overly firm work on an irritable shoulder typically causes a flare of pain lasting a day or more and can make you guard even harder. Correctly dosed massage matched to your stage does not worsen the condition.
How many sessions before massage helps a frozen shoulder?
Most people notice some pain relief after the first or second session, though it may only last a day or two at first. Longer-lasting change usually takes four to six sessions combined with a consistent home exercise program.
Is deep tissue massage safe for frozen shoulder?
It depends on the stage. During the frozen stage, when pain has settled and stiffness dominates, deep tissue work on the surrounding muscles is generally safe and useful. During the painful freezing stage it usually causes more harm than benefit.
Should I choose massage therapy or physiotherapy first?
If you have not been assessed yet, start with an assessment that can confirm the diagnosis and identify your stage. Physiotherapy with a flexibility and range of motion focus is the primary non-surgical treatment recommendation [+], with massage working best as a companion to it rather than a substitute.
Will frozen shoulder go away without any treatment?
Most cases do improve on their own, but recovery can take more than two years and some people are left with residual stiffness [+]. Treatment does not shorten that timeline, but it substantially reduces how much pain and functional loss you live with during it.
Can I have massage therapy while waiting for a specialist appointment?
In most cases yes, provided you have been medically assessed and nothing on the red flag list applies. Managing pain and preventing compensatory stiffness in the neck and upper back while you wait is a sensible use of the time.
